

TL;DR
AI in clinical data management helps most with cleaning, coding, queries and reconciliation, but it should never change EDC data alone. The model suggests, a person decides, and the audit trail records both. Teams need the help because a phase III protocol now averages 5.9 million datapoints. Regulators allow this work when each model has a clear job and validation evidence. Start with one use case you already measure, such as coding suggestions or query drafting. Run it in shadow mode, and scale only if net hours beat that baseline.
Key Takeaways
- AI in CDM works best on review-heavy tasks such as anomaly detection, coding suggestions, query drafting, reconciliation and audit trail review.
- In every task the model proposes while a named person decides, so the audit trail records both.
- Coding suggestions and query drafting make the strongest first pilots because labeled history and a human review step already exist.
- The AI layer sits beside the EDC, writes only to a review queue and then sends approved actions back through the EDC.
- Measure value as net hours, so subtract review and validation time from the gross saving before you scale.
- Regulators also expect a written context of use, validation evidence, change control and human approval for each model.

A Lab File Lands Two Days Before Interim Lock
Picture a central lab transfer arriving on a Wednesday for a phase III oncology study. Interim database lock is set for Friday. The file holds several thousand rows, and one site reports hemoglobin in g/L while every other site uses g/dL.
Two data managers split the listings and start scrolling. They flag values that look ten times too high, check reference ranges and then write queries by hand. By Thursday night they have found the unit problem, but they still have not reached the visit-date gaps further down.
The scene is illustrative, yet any CDM lead will recognize it. Nothing in it needs a person to read every row. A model could have grouped the unit outliers by site in minutes and drafted one site query for review.
The people would then spend Thursday on judgment instead of scrolling. That trade is the practical promise of AI in clinical data management. Still, it only holds when a person makes every decision that enters the record.
This guide covers where AI works in CDM and where it does not. It also shows how the pieces fit around your EDC, what regulators expect, how to measure value and how to run a first pilot.
What AI in Clinical Data Management Covers, and What It Does Not
Clinical data management turns raw trial data into a clean, locked database that statisticians and regulators can trust. AI covers one slice of that work, namely the repetitive review and drafting tasks that sit between data arriving and a person signing off.
The clearest way to define the slice is by task rather than by technology. Cleaning, coding, query handling, reconciliation, audit trail review and study build each contain a step where a model can propose something. Each also contains a step that must stay human, because an inspector will ask who made the call.
Task by Task: What AI Proposes and What People Decide
Medical coding shows the split well. Before AI, a coder searched the dictionary for every verbatim adverse event term. Now the system suggests a term with a confidence score, so the coder only accepts, edits or rejects it while remaining the person of record.
| CDM task | Traditional approach | AI-assisted approach | Human decision that stays |
|---|---|---|---|
| Data cleaning | Programmed edit checks plus manual listing review | Anomaly models flag outliers and patterns across sites and visits | Whether a flag becomes a query |
| Medical coding | Coder searches MedDRA or WHODrug for each term | Model suggests a term, together with a confidence score | The final code assignment |
| Query management | Data manager writes each query | Model drafts query text and ranks open issues by risk | Whether to send, edit or cancel |
| External data reconciliation | Side-by-side listings of lab, eCOA and safety data | Model matches records, then lists each mismatch with a likely reason | Which source is correct |
| Audit trail review | Sampled manual review | Pattern detection across the full trail rather than a sample | Whether a pattern is a real issue |
| Study build | Programmers write eCRF and edit-check specs from the protocol | Model drafts specs from protocol text before programmers review them | The validated, approved specification |
What Stays Outside CDM
Stating what AI does not cover saves arguments later. Statistical analysis and medical review sit outside CDM, even though they consume its output. Likewise, upstream research such as target selection belongs to AI in drug discovery, which is a different problem with different data.
Rules, Models and LLMs: Three Kinds of Automation
Automation in CDM comes in three kinds, and the kind decides how much validation you owe. A rule does exactly what its specification says. A learned model, by comparison, returns a probability. Large language models write text that sounds right even when it is wrong.
| Kind | Example in CDM | How it fails | How you validate it |
|---|---|---|---|
| Rules (edit checks) | Flag a visit date that falls before informed consent | Misses anything nobody wrote a rule for | Test each rule against its specification |
| Learned anomaly models | Flag a site whose blood pressure values vary less than expected | False positives, especially as enrollment changes | Measure precision and recall on labeled history, then monitor |
| Large language models | Draft a query or summarize a protocol section | Fluent but wrong text, or invented detail | Human approval of every output, as well as sampled accuracy review |
Production systems usually combine all three, while rules still do the bulk of the checking. LLMs need the most review because their failure mode is fluent error. Our guide to generative AI in healthcare shows how other clinical teams set that review up.
Why Clinical Data Management Needs AI Now
Three forces push CDM teams toward AI: more data per study, more sources per study and a regulatory model that rewards focus. Each one on its own would strain a manual process. Together, they break it.
Volume comes first. A TransCelerate and Tufts CSDD study published on December 29, 2025 found that a phase III protocol averages 5.9 million datapoints. That figure has grown about 11% a year since 2020. The same study also found that nearly one-third of procedures and datapoints per protocol are non-core or non-essential.
Variety adds to the load. Data now arrives from central labs, eCOA apps, wearables and imaging vendors, each with its own format and schedule. One CDM vendor, Saama, estimates that 40% to 70% of trial data is collected outside the EDC. Saama does not name the studies behind that range, so treat it as a vendor estimate.
Every external source needs mapping, reconciliation and its own checks. So a team that reviews each source by hand grows its workload whenever a protocol adds another device or vendor.
Regulation points the same way. ICH E6(R3) asks for a proportionate, risk-based approach to quality, and its section 4.3 covers computerized systems. Its principles and Annex 1 reached ICH Step 4 on January 6, 2025. They took effect in the EU on July 23, 2025, and the FDA published them in September 2025. Annex 2 reached Step 4 on June 3, 2026 and takes effect in the EU on January 15, 2027.
Reviewing every data point with equal effort is hard to defend under that model. It also stops scaling long before a study reaches millions of points. AI in clinical data management answers all three pressures, but only where a person stays accountable for each result.
AI Assessment
How Ready Is Your Clinical Data for AI?
Score your data foundations, governance and team readiness with Kanerika’s AI maturity assessment before you choose a first CDM use case.
Start Your AI Assessment →AI Use Cases Across the CDM Lifecycle, Ranked by Readiness
Some uses of AI in CDM already run in production, while others remain experiments. Ranking them by readiness therefore helps you pick a first pilot that can show results without a long validation fight.
Readiness here means three things hold at once. The task has labeled history to learn from, a person already reviews the output, and an error gets caught before it reaches the locked database. Coding suggestions meet all three tests, whereas autonomous data correction meets none.
| Use case | Data in | Technique | Maturity | Good first pilot? |
|---|---|---|---|---|
| Medical coding suggestions | Verbatim AE and medication terms, as well as past coding decisions | NLP classification with confidence scores | High | Yes |
| Query drafting and triage | Open discrepancies, past queries and site responses | LLM drafting, together with risk ranking | Medium to high | Yes |
| Anomaly detection | EDC and lab data across sites and visits | Statistical and machine learning outlier models | Medium to high | Yes |
| External data and SAE reconciliation | Lab, eCOA and safety database extracts | Record matching and mismatch detection | Medium | Yes, once transfer specs are clean |
| Audit trail review | Part 11 audit trails | Pattern detection | Medium | Only when the review question is defined |
| Study build from the protocol | Protocol text and standard libraries | LLM drafting of eCRF and edit-check specs | Early | Later, after a review process exists |
| Autonomous corrections | Any trial data | Agents writing directly to the EDC | Not appropriate | No |
The maturity column reflects how much review structure each task already has, rather than a vendor ranking. Anomaly detection also qualifies, but its false-positive rate needs a labeled baseline first, so coding and query drafting are the easiest starts.
The subsections below walk through each use case with an example of what the model does and what the person decides.

Data Cleaning and Anomaly Detection
Edit checks catch what someone predicted when the study was built. Anomaly detection, by contrast, looks for what nobody predicted. A typical case is a site whose vital signs vary far less than any other site’s.
Picture a site that records systolic blood pressure as exactly 120 or 130 for almost every patient. Each value passes the range check, so no edit check fires. Even so, a model that compares variance across sites flags it on the first pass.
The data manager then decides whether the cause is a rounding habit, a device problem or something that needs a monitoring visit. The model makes none of those calls. Instead, its job is to shorten the time between a pattern appearing and a person noticing it. Basic data profiling of each site’s distributions is a sensible step before any model runs.
Medical Coding With Coder Confirmation
Coding is the most mature use case because it comes with years of labeled history. Every past decision is a training example, such as a verbatim term coded to a MedDRA term by a qualified coder.
A coding assistant reads the verbatim term, suggests a lowest level term with a confidence score and then shows the path up the hierarchy. High-confidence suggestions go to a quick confirmation queue. Ambiguous terms, such as “felt off after dose,” go to a full review instead.
Two controls keep this safe. First, the coder confirms every code. Second, the team tracks how often suggestions are accepted unchanged, because a falling rate often signals that a new study’s terms differ from the training history. The same pattern also applies to medication coding against WHODrug.
Query Drafting and Triage
Query writing is slow because each query has to be specific, polite and answerable by a busy site coordinator. An LLM can draft the text from the discrepancy, the relevant protocol section and the site’s past responses.
The data manager reads the draft, edits it where needed and then sends it. Nothing reaches a site until that approval happens.
Triage is the other half of the job. The model ranks open discrepancies by their likely effect on primary endpoints and safety, so reviewers start with the issues that matter for lock. Query drafting makes a strong first pilot, since the baseline is easy to measure and every draft is reviewed anyway.
External Data and SAE Reconciliation
Reconciliation compares the same fact held in two places. Lab values in the EDC should match the central lab transfer. Similarly, serious adverse events in the EDC should match the safety database.
A matching model links records that a strict key join misses. For example, it can pair an SAE with a slightly different onset date, or a sample relabeled after a site error. It then lists each mismatch with its likely reason, while the data manager decides which source is right and raises the query.
Safety teams take over after that point with their own case processing. That workflow, from case intake to regulatory reporting, is covered in our guide to AI in pharmacovigilance.
Case Study
70% Less Manual Reconciliation for a Global Pharma Enterprise
A global pharmaceutical enterprise cut manual investigation and reconciliation time by 70% and standardized 85+ KPIs with one governed ontology on Microsoft Fabric.
Read the Case Study →Audit Trail Review
Under 21 CFR 11.10(e), electronic record systems must keep secure, computer-generated, time-stamped audit trails. A record change also may not obscure what was recorded before. Because those trails run long, teams usually sample them by hand.
Pattern detection can read the entire trail instead of a sample. It can flag data changed long after entry, bulk edits by a single user or values changed just before lock. The output is a list for a reviewer, though, never a finding on its own.
Give the model a defined question, such as late changes to primary endpoint data. Otherwise it will mostly surface noise.
Study Build: Protocol to eCRF and Edit-Check Specs
Study build turns a protocol into eCRF designs and edit-check specifications. An LLM can read the schedule of assessments and draft a first version of both, especially when your standard libraries are well kept.
The time saving is real, yet this is not a first pilot. Specifications feed a validated system, so a programmer must review every line. An error found late also costs far more than one found early, so treat study build as a second-wave use case.
Poor First Use Cases: Autonomous Corrections and Unrestricted Agents
Some ideas sound efficient until they meet the first audit. Keep these off the pilot list:
- Autonomous data corrections. A model that changes EDC values without a person breaks the chain of who decided what.
- Agents with write access to production systems. An agent that raises, closes or answers queries on its own needs controls that few teams have built so far.
- Unreviewed text sent to sites or regulators. Fluent text is not proof of accuracy, so every outbound draft needs a reader.
- Models reused across studies without revalidation. Terms, visits and endpoints change from one protocol to another.
Agents are not off limits forever, but they need a human approval step and clear guardrails for AI agents. Claims teams face the same question. Our guide to AI agents for insurance claims processing shows how approval queues keep an agent useful without letting it act alone.
Talk to Kanerika
Choosing Your First Clinical Data AI Pilot?
Kanerika will help you rank CDM use cases against your own baseline, write the context of use and design a review queue that keeps every decision with your team.
Schedule a Demo →Worked Example: From a Lab Transfer to a Reviewer-Approved Query
Go back to the lab file from the opening scene. Here is how the same transfer moves through an AI-assisted process, with the approver named at each step.
- The file arrives. The transfer lands in a staging area, where an automated rule confirms it matches the data transfer agreement. Approver: none, since a rule runs this check.
- Mapping. Values are mapped to the study’s standard structure, such as the SDTM lab domain. Approver: a data manager signs off on any new mapping.
- Anomaly pass. A model compares units, ranges and distributions by site. It then flags one site’s hemoglobin values as a likely unit mismatch. Approver: none yet, because a flag is not a decision.
- Grouping. The system groups the flagged rows into a single site-level issue rather than one discrepancy per row. Approver: the data manager confirms the grouping.
- Draft query. An LLM drafts one query asking the site to confirm the unit, citing the protocol and the affected rows. Approver: the data manager edits and sends it.
- Site response. The site confirms g/L, so the lab vendor corrects the transfer. Approver: the data manager closes the query.
- Audit trail. Every step, including the model’s flag and each human approval, is recorded with a timestamp and a user. Approver: quality assurance during review.
What Made the Example Work
The model saved time in steps 3 to 5, yet it made no decision that changed trial data. People approved the mapping, the query and the closure, which is exactly what an inspector will look for.
The lab transfer had a written specification, past unit errors were labeled, and a review queue already existed. Without those three things, the same model would mostly produce noise.
How the Architecture Fits Around Your EDC, CTMS and eTMF
AI for CDM works as a helper layer beside the EDC, which stays the system of record. The layer reads copies of the data and writes suggestions to a review queue. Approved actions then go back through the EDC, so the audit trail stays intact.
A typical layout has five layers. Sources include the EDC, CTMS, eTMF, lab and eCOA transfers, as well as the safety database. A staging layer lands copies and maps them to standards such as SDTM, and then models run on that staged data.
Model output goes to a review queue where data managers, coders and programmers act on it. The final layer is the one teams most often get wrong. Approved actions, such as a sent query, go through the EDC’s own functions and never through a direct database write.
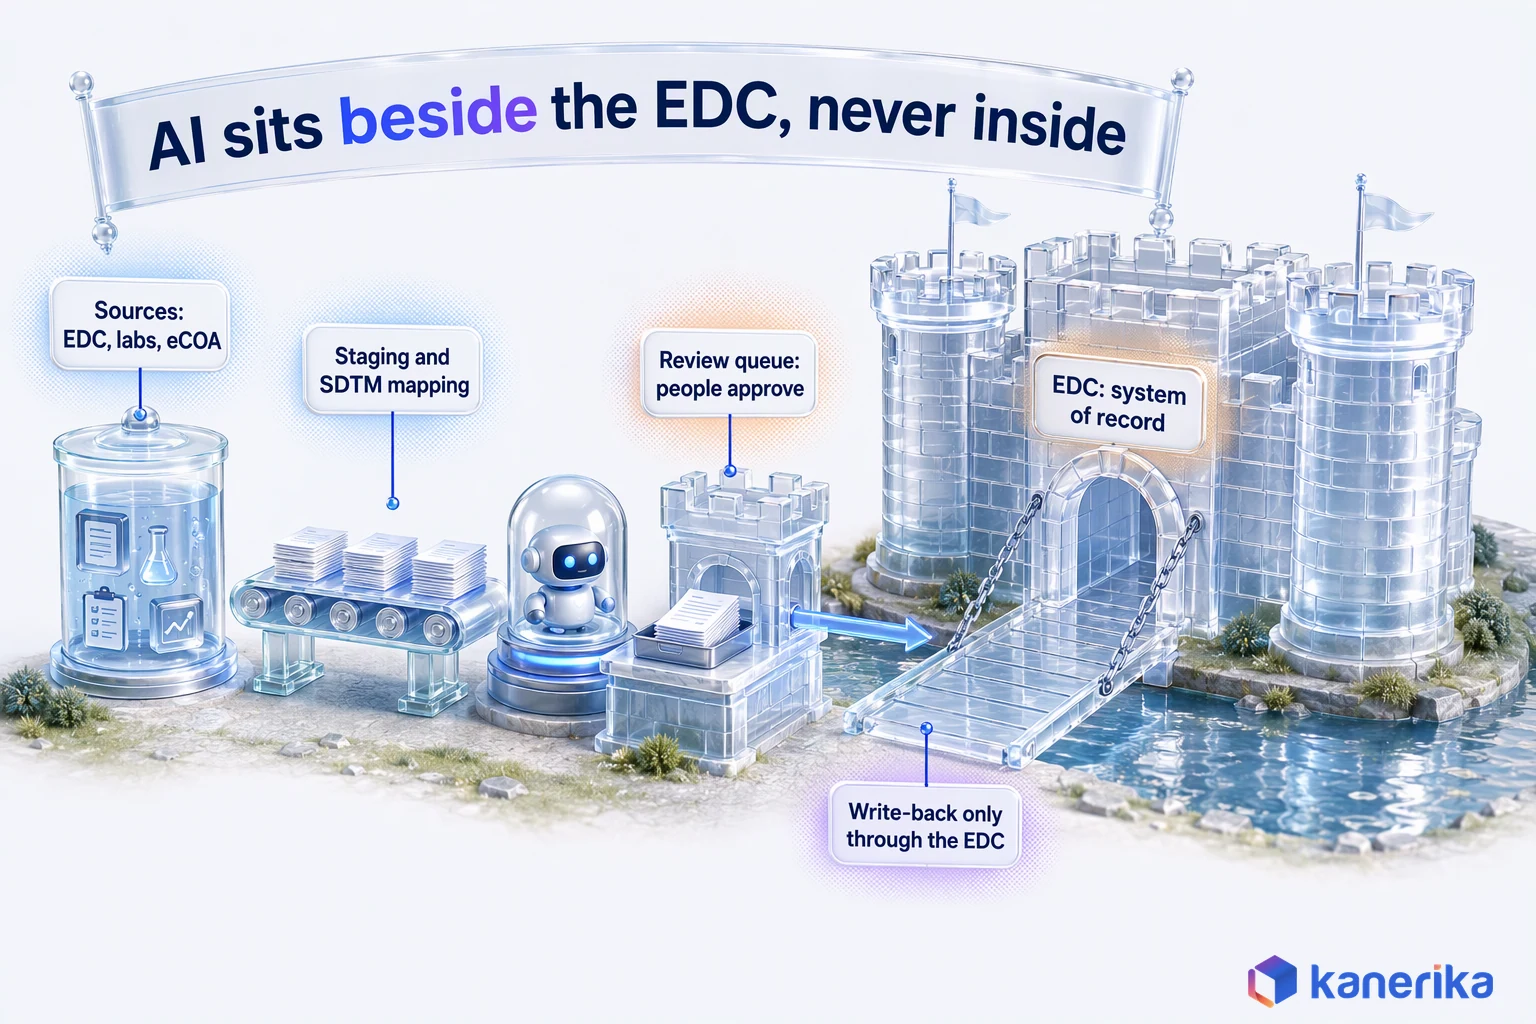
That design keeps the EDC as the system of record, so Part 11 controls apply exactly as they did before. The CTMS and eTMF play supporting roles. The CTMS supplies site and visit context for triage, while the eTMF stores each model’s validation evidence where an inspector can find it. All of this belongs in a wider healthcare data strategy that decides which platform holds which record.
Data Prerequisites: Access, Context and Labeled History
A model can only be as good as the history it learns from, and bad data quality shows up first as false flags. So before any build starts, confirm that these pieces are in place:
- Access. Read access to EDC exports and external transfers, cleared by privacy and quality teams before any model reads them.
- Context. Data transfer specifications, the protocol and edit-check specs, so the model knows what normal looks like.
- Labeled history. Past queries with outcomes and past coding decisions, which then become the ground truth for testing.
- Standards. Consistent mapping to CDISC structures, so that a model can work across studies. Our guide to data standardization covers the wider practice.
- A review queue. One place where people approve or reject outputs, while every action is logged.
Build, Buy or Extend: Choosing Your Approach
Once a use case is chosen, the next question is where the AI comes from. There are three paths, and each one trades control against validation effort.
Extending your EDC vendor’s AI features is fastest when the vendor already supports the use case, because validation evidence often comes with the product. A specialist CDM product suits teams that need a capability the EDC lacks, such as anomaly detection across studies.
A custom build on your own data platform gives the most control and also works across EDC vendors. The catch is that you then own every line of validation.
| Criterion | Extend EDC vendor AI | Specialist product | Custom on your data platform |
|---|---|---|---|
| Validation burden | Lowest, since the vendor supplies evidence | Medium, shared with the vendor | Highest, because you own it |
| Data volume and sources | Limited to EDC data | Usually several sources | Any source you can land |
| Integration effort | Native | Connectors needed | You build it |
| Cost profile | License add-on | License plus integration | Build and run cost |
| Control over models | Low | Medium | Full |
| Best fit | Single-EDC sponsor with standard use cases | Sponsor or CRO with one specific gap | Multi-EDC portfolios, especially with custom analytics |
Many sponsors end up with a mix, using vendor coding features alongside a custom anomaly layer that spans studies. Whichever path you take, the pilot gates below stay the same.
Kanerika Service
AI for Pharma and Life Sciences
Kanerika designs governed AI for regulated pharma data, from data preparation and PHI redaction to validated models with human approval built in.
Explore AI for PharmaFive Gates Before You Approve a Pilot
A pilot that skips these gates tends to stall during validation. Treat each one as a yes or no test before you fund a use case.
- A baseline exists. You know the current hours, cycle times or backlog for the task before the model arrives.
- The context of use is written. One page states what the model does, what it does not do and who approves its output.
- Data access is cleared. Privacy, quality and the data owner have signed off on what the model reads.
- A validation plan is agreed. It names the test set, the acceptance criteria and who signs the report.
- A human sign-off path is built. Every output lands in a queue where a named role approves it, with the action logged.

Worked Decision: Query-Drafting Assistance
Run query drafting through the five gates. The baseline is simple because your EDC already records how long each query takes from open to close. The context of use also fits in two lines: the model drafts, and the data manager sends.
Data access is the gate that needs the most work in this case. Past queries and site responses may contain free text with patient details, so redaction has to come first. Until that step is done, the gate stays closed.
The validation plan tests drafts against a held-out set of past queries, scored by the data managers who will use the tool day to day. The sign-off path already exists, since no query leaves until a person sends it. All five gates pass, which makes query drafting a sound first pilot.
Measuring Value: KPIs, Cost and Effort Before You Scale
Value has to be measured against your own baseline rather than a vendor’s headline. Pick two or three KPIs per use case and track them from shadow mode onward. Shadow mode gives a clean comparison, since the model runs beside the current process without changing it.
| KPI | What it measures | Use case it tracks |
|---|---|---|
| Query cycle time | Days from query open to close | Query drafting and triage |
| Auto-coding acceptance rate | Share of suggestions accepted unchanged | Medical coding |
| Reconciliation backlog | Open mismatches at a point in time | External data and SAE reconciliation |
| False positive rate | Share of flags that reviewers dismiss | Anomaly detection, as well as audit trail review |
| Time to database lock | Days from last patient visit to lock | All use cases, as the end measure |
A Simple Formula for Net Hours Saved
Effort needs a formula you can defend, built only from numbers your team can measure. Net hours saved equal baseline hours, times the share of items AI handles, times the acceptance rate, minus review and validation hours.
Here is an illustrative example with assumed numbers rather than a benchmark. Say a team spends 400 hours a month writing queries. AI drafts 60% of them, or 240 hours of work. Data managers accept 70% of those drafts with light edits. That gives 400 x 0.6 x 0.7, or 168 gross hours.
Now subtract the cost of oversight. If reviewing drafts takes 40 hours a month and validation upkeep averages 30 hours, then the net saving is 98 hours a month.
That saving is still worth having. It is also far below the 240 hours a headline would claim by counting every drafted query as time saved. So put your own numbers into the same formula during shadow mode. If the net figure is small, fix the model or pick another use case before you scale.

Regulation and Governance for AI in Clinical Data Management
Regulators treat an AI model like any other computerized system, plus one extra test: is it credible for its specific job?
The FDA set out that test in its January 2025 draft guidance on AI to support regulatory decision-making for drugs and biological products. It describes a risk-based, step-by-step credibility assessment tied to a defined context of use. As of November 13, 2026 the guidance was still marked as a draft, not for implementation.
Context of use is the idea that ties these documents together. A model cleared to suggest codes for one study is not cleared to change data, or to run on another study, until new evidence exists.
In January 2026 the FDA and EMA jointly issued 10 guiding principles of good AI practice in drug development. They cover data governance and documentation, risk-based performance assessment and life cycle management. For a wider view of risk-tiered AI oversight across providers and payers, see our guide to AI governance in healthcare.
US and Global Reference Checklist
The rules below are the ones a CDM quality team will be asked about first. Treat the table as a starting map for your quality and legal teams rather than as legal advice.
| Rule | What it asks | What it means for AI in CDM | Date |
|---|---|---|---|
| 21 CFR Part 11, section 11.10(e) | Secure, computer-generated, time-stamped audit trails that never obscure earlier entries | Log every model suggestion and human approval, then write back only through the EDC | In force |
| ICH E6(R3) | Proportionate, risk-based quality, with section 4.3 on computerized systems | Validate AI tools in proportion to their risk to participants and data | Principles and Annex 1: Step 4 on January 6, 2025, EU effective July 23, 2025, FDA published September 2025. Annex 2: Step 4 on June 3, 2026, EU effective January 15, 2027 |
| FDA draft guidance, docket FDA-2024-D-4689 | Risk-based credibility assessment for a defined context of use | Write a context of use and a credibility plan for each model before use | Draft issued January 2025 |
| FDA and EMA guiding principles | 10 principles of good AI practice in drug development | Document data governance, performance testing and life cycle management | Issued January 2026 |
| EMA reflection paper, EMA/CHMP/CVMP/83833/2023 | Use of AI across the medicinal product life cycle | Applies to EU studies and submissions | First published September 30, 2024 |
| HIPAA, 45 CFR 164.514(b) | De-identification by expert determination or safe harbor | De-identify or redact PHI before model training or prompting | In force |
Protecting Patient Data: PHI and De-Identification
Trial data is usually pseudonymized, but free text is where patient details slip through. Query responses, adverse event verbatims and site comments can all contain names, dates or record numbers.
HIPAA’s de-identification standard in 45 CFR 164.514(b) sets out two routes. Expert determination relies on a qualified expert to confirm that the risk of re-identification is very small. Safe harbor, on the other hand, removes 18 listed identifiers, including names, most dates and record numbers.
For model training and LLM prompts, redact free text before it leaves the controlled environment. Log what was removed, and test the redaction on a sample each time a new data source joins.
Detection usually relies on named entity recognition to find names, dates and record numbers in text. Services expose the settings that matter here. In the 2025-11-15-preview of Azure Language PII detection, confidenceScoreThreshold takes a default value plus per-entity overrides. The entityMask redaction policy swaps each finding for its type, such as [PERSON_1], so a coding or query model still sees the sentence structure.
A Minimum Governance Package for Production
Before a model moves from pilot to production, assemble a package an inspector could read in an hour. It does not need to be long, but every item must exist and stay current.
- Context of use. What the model does, for which studies and with which approver.
- Validation evidence. The test set, acceptance criteria and results, together with the signed report.
- Change control. How a retrained model or a new prompt gets tested and approved before release.
- Monitoring. Acceptance rates, false positives and drift, reviewed on a fixed schedule as part of AI model risk management.
- Audit trail. Every suggestion, approval and write-back, with a timestamp and a user.
- Human approval log. Who approved what, and on what evidence.
The package belongs inside your wider data governance program rather than beside it. Our guide to data governance in healthcare covers ownership, quality rules and stewardship at that broader level.
Checklist
AI Governance Checklist
Check context of use, validation, change control, monitoring and approval logging before a clinical data model moves from pilot to production.
Get the Checklist →Common Mistakes and How to Avoid Them
The same few mistakes slow early CDM pilots again and again. Each has a simple fix when you catch it before the build starts.
- Starting with the hardest use case. Begin with coding or query drafting instead, since review already exists there.
- Counting gross time saved. Subtract review and validation hours from the first report onward.
- Skipping shadow mode. Run the model beside the current process before it touches live work.
- Treating a vendor’s validation as your own. Test on your own studies, then document the result.
- Sending raw free text to an external model. Redact first and keep a record of what was removed, or run private LLMs inside your own environment.
How the Clinical Data Manager Role Changes
AI keeps the clinical data manager accountable, yet it changes what a good day looks like. The work moves from reading every listing to supervising exceptions and the models that surface them.
Coding shows the shift clearly. A coder who once assigned every term now confirms high-confidence suggestions quickly. Meanwhile, the real time goes to the ambiguous terms. Query work moves the same way, from drafting text to judging which issues matter for lock.
New skills follow from that change. Data managers need to read model metrics such as precision and acceptance rates. They also need to write clear context-of-use statements and spot drift when a new study looks unlike the training data.
The role gains a governance duty as well. Someone has to own the review queue, sign off on model changes and explain both to an inspector. That person is usually a senior data manager rather than an IT lead.
Looking further ahead, software will propose more of the steps as agents mature. The data manager’s value will then come less from doing each check and more from deciding which proposals to trust. A healthcare operations team saw this shift when AI took over routine document checks. The checks reached 90% accuracy and cut wastage by 64%, as the video below shows.
How Kanerika Delivers Governed AI for Clinical Data
Kanerika builds AI for regulated data work around one rule: the model proposes, a named person decides and the record shows both. For clinical data, that rule shapes a five-stage delivery approach.
- Discover and baseline. Pick one use case, measure current hours and cycle times, and then write the context of use.
- Prepare data and controls. Land EDC and external data, map it to standards and redact PHI before any model reads it.
- Build in shadow mode. Run the model beside the current process, so it has no effect on live data.
- Validate and pilot. Test against labeled history, agree acceptance criteria and then pilot on one study.
- Scale and operate. Add monitoring and change control before you bring in the next use case.
Proof From Clinical and Pharma Data Work
The approach comes from real clinical data work. A provider of advanced analytics and clinical research services, operating in over 100 countries, relied on manual SAS programming to convert raw trial data. Data cleaning was slow, and pulling data from diverse sources limited what its teams could analyze.
Kanerika integrated Trifacta for extraction, transformation and cleaning, with reusable flows that adapt to new data formats and sources. The new flows also skipped the intermediary databases the team had used for extraction, which raised the quality of research data.
According to the case study, the result was a 60% reduction in processing time. Decision-making speed improved by 35%, user productivity by 45% and operational efficiency by 40%.
Reconciliation work follows the same pattern, as the governed ontology on Microsoft Fabric case study earlier in this guide shows.
Clean, unified data comes before any model. A multinational pharmaceutical company struggled with inaccurate and inconsistent data spread across systems. Kanerika designed a data lake serving more than 15 use cases, with continual data quality checks and rebuilt data pipelines. Data accuracy rose 40% and response times fell 45%, as described in this pharma data platform case study.
Patient data gets the same care. Kanerika’s Susan agent redacts PII from documents without storing them and supports GDPR, CCPA and HIPAA compliance. It therefore fits the redaction step before any model reads free text.
Teams can start with Kanerika’s AI services or its work in AI for pharma and life sciences. Either route begins with the same first step: one use case, one baseline and one governed pilot.
Case Study
60% Faster Clinical Trial Data Processing
A clinical research services provider in over 100 countries replaced manual SAS programming with automated data preparation, cutting processing time by 60% and speeding decisions by 35%.
Read the Case Study →Where Does AI Belong in Clinical Data Management?
AI belongs in the review-heavy middle of CDM, such as cleaning, coding, query drafting, reconciliation and audit trail review. It does not belong anywhere it would change trial data without a person deciding.
The first step is deliberately small. Choose one use case with a measured baseline, pass it through the five gates and then run it in shadow mode. If net hours beat the baseline after review and validation, scale it to the next study.
That is the working answer for AI in clinical data management: the model proposes, the data manager decides, and one governed pilot proves whether it pays.
Frequently Asked Questions
What is AI in clinical data management?
AI in clinical data management uses machine learning, natural language processing and language models to help clean, code, query and reconcile clinical trial data. The model proposes a flag, a code or a draft query. A data manager, coder or programmer reviews it and decides. Both steps are logged, so the trial database stays inspection-ready.
Is AI allowed in regulated clinical trials?
Yes. No US or EU rule bans AI in trial data work. Regulators expect the controls that apply to any computerized system, such as Part 11 audit trails and validation. They also expect a defined context of use and evidence that the model is credible for that job. A person must still own every decision.
How does AI handle data from wearables, eCOA and other non-EDC sources?
External data first lands in a staging layer and is mapped to standards such as SDTM. Models then check ranges, units and patterns and match records against the EDC. Mismatches go to a review queue with a likely reason for each one. The data manager decides which source is right and raises any query through the EDC.
What does 21 CFR Part 11 require when AI touches trial data?
Part 11 requires secure, computer-generated, time-stamped audit trails, and a change may never obscure the earlier entry. When AI is involved, log every model suggestion and every human approval. Send approved changes back through the EDC rather than writing to the database directly. That keeps the EDC as the system of record for inspectors.
Should we build, buy or extend our EDC vendor's AI features?
Extend your EDC vendor’s features when they already cover the use case, since validation evidence often comes with them. Buy a specialist product for a capability the EDC lacks. Build on your own data platform when you run several EDCs or need full control. Many sponsors combine vendor coding features with a custom anomaly layer.
How does AI help with medical coding in clinical data?
A coding assistant reads each verbatim adverse event or medication term and suggests a MedDRA or WHODrug code with a confidence score. High-confidence suggestions go to a quick confirmation queue, while ambiguous terms get full review. The coder confirms every code. Teams track the acceptance rate to spot when a new study drifts from the training history.
How does AI protect patient data and PHI in clinical trials?
AI protects patient data only when the pipeline is built for it. Free text such as query responses and site comments should be redacted before any model reads it. HIPAA allows de-identification by expert determination or by removing 18 listed identifiers. Teams should log what was removed and test redaction on every new data source.
What are the main benefits of AI in clinical data management?
The main benefits are faster review and better focus. Models scan every record for anomalies, draft queries, suggest codes and match external data, so people spend time on judgment instead of scrolling listings. The measurable results show up as shorter query cycle times, smaller reconciliation backlogs and a faster path to database lock against your own baseline.
What are the biggest challenges when adopting AI in CDM?
The biggest challenges are validation effort, data access and measurement. Each model needs a written context of use and test evidence. Free text often holds patient details, so redaction must come first. Teams also tend to report gross time saved and ignore review hours. Starting with one well-baselined use case avoids most of these problems.
How long does it take to deploy AI in clinical data management?
Timing depends on the use case and on how ready the data is. Kanerika runs five stages, namely discover and baseline, prepare data and controls, build in shadow mode, validate and pilot, then scale. A use case with clean history and an existing review queue moves through them faster than one that needs new data feeds.
How do you validate an AI model used in clinical data management?
Start with a written context of use that says what the model does and who approves its output. Test it against a held-out set of labeled history, such as past queries or coding decisions, with agreed acceptance criteria. Record the results in a signed report. Then monitor acceptance rates and drift, and retest after every change.
Will AI replace clinical data managers?
No. AI changes the job rather than removing it. Data managers move from reading every listing to supervising exceptions, reviewing model output and owning the review queue. They also need new skills, such as reading precision and acceptance metrics and spotting drift. Regulators still expect a named person to make every decision that enters the record.
Which clinical data management use case should we pilot first?
Pick a use case with labeled history, an existing human review step and a measurable baseline. Medical coding suggestions and query drafting usually fit best, because every output is already reviewed. Anomaly detection is a close third. Avoid study build and anything that writes to the EDC on its own until a working review process exists.













