

TL;DR
Data governance in healthcare fails as a HIPAA binder or a tool purchase, and it works when named owners enforce the rules. It is the set of decision rights, standards and controls for patient, claims and operational data. The fix is to name an owner for each data domain and put every rule where the data is used. A single community hospital should run a centralized model. A multi-hospital system or academic medical center needs a hybrid, while a multi-line payer federates owners under central standards. Start with one domain and one live use case, then report owner coverage and quality pass rates within 90 days.
Key Takeaways
- Data governance in healthcare decides who owns patient, claims and operational data, what each field means and who may use it.
- HIPAA compliance is one input to governance, not the whole of it, because HIPAA does not define a readmission or name a steward.
- Two root failures drive the rest: a council with no decision rights and domains with no named owner. Buying a catalog first is their most visible symptom.
- US rules such as 42 CFR Part 2, information blocking and the CMS interoperability rule each require evidence that only governance can produce.
- Pick the operating model by organization type: centralized for one hospital, hybrid for a system, federated for a multi-line payer.
- Prove progress with owner coverage, quality pass rates and access approval time, starting on one domain within 90 days.
One Patient, Three Records, No Agreed Owner
Picture a quality meeting at a mid-sized health system. The readmission dashboard says 412 patients came back last quarter. Finance, however, says 389, while the care-management team says 455. Every number comes from a real system, and every analyst can defend their query.
The EHR, for example, counts any inpatient return. Claims counts only paid encounters, so it misses the patients whose bills are still open. Care management, meanwhile, includes observation stays because those patients still needed follow-up calls.
Nobody in the room can say which number is right, because nobody owns the definition of a readmission. The meeting ends with an action item to “align the data,” which usually means a fourth spreadsheet. The scene is illustrative, but any healthcare analytics lead will recognize it.
That gap is what data governance in healthcare exists to close. It has little to do with a policy binder and everything to do with who decides, what they decide and how the decision is enforced.
What Is Data Governance in Healthcare?
Data governance in healthcare is the operating model for health data. It decides who owns each kind of data, what it means and who may use it for what purpose. It turns those decisions into controls that run where the data lives, so the answers do not depend on who wrote the query.
Think of it as decision rights plus enforcement. Decision rights say that the chief nursing officer, for example, owns the definition of a fall event. Enforcement means the reporting platform only publishes fall rates calculated from that definition, and it blocks the ones that are not.
Healthcare also adds pressure that other industries do not face. Protected health information carries federal privacy rules, clinical data drives treatment decisions, and claims data drives revenue. The same patient appears in the EHR, the billing system, the lab system and often a payer feed, each with its own identifier.
The general principles of a data governance framework still apply here. What changes is the size of the stakes and the number of rules to map. The sections below cover both in order.
Data Governance in Healthcare vs Data Management, Security and HIPAA
These four terms get used interchangeably in steering meetings, and that confusion is the root of several mistakes later in this guide. Each one answers a different question and usually has a different owner. The split between data governance and data management causes the most confusion.
| Discipline | Question it answers | Typical owner | Healthcare example |
|---|---|---|---|
| Data governance | Who decides what this data means and who may use it? | Governance council and domain owners | The CMO approves the system-wide definition of a 30-day readmission |
| Data management | How is the data stored, moved and maintained? | Data engineering and IT | Pipelines load ADT feeds from the EHR into the warehouse every hour |
| Data security | How is the data protected from unauthorized access? | CISO and security team | Encryption, network controls and multi-factor sign-in for the analytics platform |
| HIPAA compliance | Does our handling of PHI meet federal privacy and security rules? | Privacy and compliance officers | Business associate agreements and breach notification procedures |
Governance therefore sits above the other three. It tells data management which definitions to build, tells security which roles need which access, and gives compliance the evidence it needs for an audit.
Case Study
90% Compliance Adherence for Healthcare with Purview
A top North American healthcare organization classified data across Azure, SQL and SaaS sources with Microsoft Purview, cutting data discovery time by 57% and lifting compliance adherence by 90%.
Read the Case Study →Why Healthcare Data Governance Matters More in 2026
Healthcare data now gets reused far beyond the encounter that created it, and every reuse raises the same question of permission and meaning. A discharge summary written for one patient may later feed a quality measure, a payer quality program, a research cohort and a language model. That reuse is why governance belongs inside any healthcare data strategy.
Three outside forces make that reuse harder to manage informally. First, AI teams want large volumes of clinical data, often faster than privacy reviews can move, so unreviewed extracts pile up in sandboxes.
Second, federal rules now carry fixed dates. Part 2 compliance has applied since February 2026, and most CMS payer API requirements land on January 1, 2027. Each rule asks for evidence that only named owners and access logs can produce.
Third, breaches stay expensive. The IBM Cost of a Data Breach Report 2026 puts the global average at USD 4.99 million, up 12% on the prior year. Without a classified inventory, the privacy team cannot quickly say which datasets a breach exposed.
A fourth pressure comes from inside. Many health systems have grown by acquisition, so they run several EHR instances and billing platforms side by side. Without governance, each merger or data migration in healthcare adds another set of definitions to reconcile. The readmission meeting above then repeats with every new hospital.
What Good Governance Changes for Care, Cost and Risk
The benefits show up in places that leaders already track, which makes them easier to fund than an abstract “data maturity” goal. Go back to the readmission meeting. Once the CMO publishes one owned definition, the 412, 389 and 455 debate ends, and clinicians act on the number instead.
Privacy risk drops the same way. When data is classified and every access is logged, the privacy team can answer “who saw this record and why” without a forensic project.
- Revenue integrity: consistent coding and encounter data reduce claim denials that start as data mismatches between clinical and billing systems.
- Interoperability: standard terms and mapped code sets make exchange with payers, HIEs and other providers less manual.
- Analytics and AI speed: approved, documented datasets let teams doing data analytics in healthcare start in days, not after a fresh legal review.
The US Rules and Standards Your Governance Program Has to Map To
US healthcare regulation does not prescribe a governance framework, but almost every major rule assumes one exists. The rules below ask an organization to prove something about its data, and that proof has to come from owners, classifications and logs.
The table summarizes what each rule means for governance work as of November 13, 2026. Treat it as a planning aid for governance work, and confirm legal obligations with counsel.

Privacy and Security Rules
Privacy rules decide who may see health data and under what conditions. Most teams know these rows well, yet each one still needs a named owner and stored evidence.
| Rule or standard | Who it applies to | What governance must prove | Date or status |
|---|---|---|---|
| HIPAA Privacy and Security Rules | Covered entities and business associates | PHI is classified, access follows minimum necessary, and safeguards are documented | In force |
| HIPAA Security Rule proposed update | Covered entities and business associates | Asset inventories and stronger technical controls, if finalized | Proposed January 6, 2025; no final rule found as of November 13, 2026 |
| 42 CFR Part 2 final rule | Federally assisted substance use disorder programs and recipients of their records | SUD records are tagged, consent is tracked and redisclosure is controlled | Effective April 16, 2024; compliance by February 16, 2026 |
Take Part 2, for instance. A health system that runs a federally assisted addiction program has to tag those records. Then the analytics platform can keep them out of general cohorts unless consent allows otherwise. That tag is a governance decision long before it is a technical one.
Interoperability and Exchange Rules
Exchange rules push the other way, since they require data to flow to patients, payers and partners. Governance has to make sure that flow is both accurate and permitted.
| Rule or standard | Who it applies to | What governance must prove | Date or status |
|---|---|---|---|
| Information blocking (45 CFR Part 171) | Providers, health IT developers, HIEs and HINs | Any refusal to share electronic health information fits a defined exception | In force under the 21st Century Cures Act of 2016 |
| CMS Interoperability and Prior Authorization Final Rule (CMS-0057-F) | Impacted payers such as Medicare Advantage and Medicaid plans | Prior authorization and patient data are accurate and available through APIs | Certain provisions from January 1, 2026; most API requirements by January 1, 2027 |
| CMS drug prior authorization proposed rule | Impacted payers | Electronic prior authorization for drugs and API endpoint reporting, if finalized | Proposed April 14, 2026; comments closed June 15, 2026 |
| TEFCA | Participants exchanging through a QHIN | Exchange purposes and data use match the Common Agreement | First QHINs designated December 2023 |
| ONC HTI-1 algorithm transparency | Developers of certified health IT and their customers | From December 28, 2026, certified EHRs need not expose predictive-tool source attributes, so model provenance becomes the organization’s own record | HTI-1 source-attribute requirements removed by the ONC final rule of October 28, 2026, effective December 28, 2026 |
State privacy laws and, for international research partners, GDPR may also apply. The practical point is that each row needs a named owner and a piece of evidence. That is why the rules map becomes the council’s first backlog.
The Building Blocks of a Healthcare Data Governance Framework
A working framework has five parts, and each one depends on the one before it. Owners come first because every later piece, from definitions to access rules, needs someone with the authority to approve it.
The five blocks below are the minimum. Larger organizations add more, such as a separate research data office, but they rarely succeed by skipping one of these.

Decision Rights: Council, Domain Owners and Stewards
Governance roles work when each one maps to a decision, not a meeting. A council that only reviews slides will drift, while a council that approves definitions and resolves conflicts between domains has a real job. Stewards matter just as much, as this guide to data stewardship explains.
| Role | Decides | Typical person |
|---|---|---|
| Executive sponsor | Funding, priorities and escalations that cross departments | CEO, COO or CFO |
| Chief data or analytics officer | Program scope, standards and the order in which domains are governed | CDO, CDAO or VP of analytics |
| Governance council | Enterprise definitions, policy approvals and conflicts between domains | Leaders from clinical, finance, IT, privacy and quality |
| Domain owner | Meaning, quality thresholds and permitted uses for one domain | CNO for nursing data, revenue cycle VP for claims |
| Data steward | Day-to-day rule upkeep, issue triage and glossary entries | Clinical informaticist or senior analyst |
| Data custodian | How controls are built and run in the platform | Data engineer or platform administrator |
The privacy officer and CISO sit on the council but do not own domains. Their job is to set the guardrails that every domain owner works within, which keeps compliance from becoming the default owner of everything.
Data Domains: Clinical, Claims, Patient Access, Research and Operations
A domain is simply a group of data with one accountable owner and one set of rules, so each decision has a clear home. Splitting health data into domains keeps the council from trying to govern everything at once, which is how many programs stall in their first year.
Five domains cover most providers and payers.
- Clinical: encounters, diagnoses, orders, results and notes from the EHR and ancillary systems.
- Claims and revenue: charges, claims, remittances and denials, the domain behind AI agents for insurance claims processing.
- Patient access and identity: registration, demographics, consent and the master patient index.
- Research: cohorts, trial data and de-identified extracts, including work on AI in clinical data management.
- Operations: staffing, supply chain, scheduling and facility data.
Pick the first domain by pain, not by size. If the readmission debate is what keeps leaders up at night, clinical encounter data is the place to start.
Talk to Kanerika
Not Sure Which Data Domain to Govern First?
Kanerika will map your clinical, claims and access data, name the decisions each owner needs to make and pick a first domain you can govern in 90 days.
Schedule a Demo →Standards, Definitions and Interoperability
Standards are where governance meets the outside world. Internally, a business glossary records what each term means, who approved it and which systems calculate it. Externally, the program has to align those terms with the standards that regulators and partners expect.
In US healthcare, that means HL7 FHIR for API exchange. It also means the United States Core Data for Interoperability (USCDI), which lists the data classes certified systems must support. Code sets such as ICD-10, CPT, LOINC and SNOMED CT matter as well. Governance decides which internal codes map to which standard, and it assigns an owner to keep each map current.
A glossary entry is only useful when it is specific. “Readmission” should state the window, which encounter types count, what is excluded and the source system of record. Once approved, the same entry should appear in the catalog next to every dataset that uses it.
Data Quality Rules Clinicians Will Trust
Clinicians trust data quality rules when the rules check things a clinician would also check. A rule that a discharge cannot come before an admission makes sense to a nurse, whereas a rule called “completeness score 0.93” usually does not.
Good healthcare quality rules share a few traits, and a broader data quality framework adds more.
- A good rule protects a named critical data element, such as discharge date or primary diagnosis.
- The threshold is one the domain owner approved, for example at least 99% of encounters passing.
- Failures route to a steward with the record IDs, not to a generic IT queue.
- Results are published next to the dataset, so report users see the current pass rate.
- Rules run before data reaches a certified report, not after a clinician spots the error.
For example, here is a worked check that a steward might schedule against an encounter table. It returns the share of inpatient encounters where the discharge date is missing or falls before admission.
-- Quality rule QR-ENC-004: discharge must follow admission
SELECT
  COUNT(*) AS inpatient_encounters,
  SUM(CASE WHEN discharge_ts IS NULL
            OR discharge_ts < admit_ts THEN 1 ELSE 0 END) AS failing_rows,
  ROUND(100.0 * SUM(CASE WHEN discharge_ts IS NULL
            OR discharge_ts < admit_ts THEN 1 ELSE 0 END)
        / NULLIF(COUNT(*), 0), 2) AS fail_pct
FROM clinical.encounters
WHERE encounter_class = 'inpatient'
  AND encounter_status = 'finished';
If the domain owner set a threshold of 99% passing, any fail_pct above 1.00 blocks the readmission dataset from certification. The steward then gets the failing encounter IDs and a ticket, while the report keeps showing the last certified version.
Metadata, Lineage and the Catalog
Metadata and lineage answer the two questions auditors and analysts ask most: what is this field, and where did it come from? Without them, every report review turns into a hunt through pipeline code.
A catalog holds the inventory of datasets with their owners, classifications, glossary terms and quality scores. Data lineage then traces how a number on a dashboard was built, from the EHR table through each transformation. When a source system changes a code set, lineage shows which reports and models will break.
For healthcare, the catalog also has to show sensitivity. A dataset tagged as containing PHI or Part 2 records should carry that tag downstream, so derived tables inherit the same access rules. On Microsoft platforms, catalog and lineage move to the Fabric OneLake catalog under Microsoft’s November 12, 2026 retirement notice for Purview Data Governance. Microsoft Purview still applies the sensitivity classifications, as the video below shows.
What Most Healthcare Teams Get Wrong and What to Do Instead
Picture a data catalog a year into its license: thousands of tables listed, and the owner field blank on nearly every one. The effort went into the visible parts, such as committees, policies and tools, while the parts that change behavior stayed empty.
The eight mistakes below come up again and again in health systems and payers, and they overlap with wider data governance challenges. Each one also has a symptom you can spot in a single meeting and a fix that does not require a new budget line.
The Eight Mistakes at a Glance
| Mistake | What you see | What to do instead |
|---|---|---|
| A committee with no decision rights | Monthly meetings, slide reviews and no approved definitions | Give the council a charter to approve definitions and settle conflicts, with a decision log |
| Tool bought before owners exist | A catalog full of tables with blank owner and description fields | Name domain owners and critical data elements first, then load the catalog |
| HIPAA compliance treated as governance | The privacy office owns every data question by default | Keep privacy as a guardrail and give meaning and quality to domain owners |
| No business owner per domain | IT gets blamed for clinical definitions it never chose | Assign each domain to an executive who uses the data, such as the CNO |
| Policies with no enforcement point | Policies live in SharePoint while reports use any table they like | Enforce each policy in the platform through access rules, certification or blocked publishing |
| Secondary use and AI ignored | Data science teams copy clinical extracts into sandboxes with no review | Add permitted-use review, provenance records and logged access for analytics and AI |
| De-identification assumed, not tested | Extracts labeled “de-identified” still hold dates, ZIP codes or free text | Choose Safe Harbor or Expert Determination per extract and keep the evidence |
| No metrics | Leaders cannot tell whether governance is working, so funding fades | Report owner coverage, quality pass rates and access approval time each quarter |
The Two Mistakes Behind the Rest
Two of these mistakes cause most of the others. A council with no decision rights cannot name owners. Without owners, a catalog, a policy set or a metric has nobody to answer for it.

Consider a council that reviews the readmission definition for six months. Each meeting ends with comments, because its charter lets it discuss definitions but not approve them. The CMO and the CFO keep their own versions in the meantime, and the dashboard keeps showing three numbers.
The second root looks different on the ground. When nursing data has no executive owner, a rising fall rate lands on IT, which only moved the data. Nobody with clinical authority decides whether a fall without injury counts, so the number keeps shifting and nobody fixes it.
The other six rows each map to a later fix. Untested de-identification is covered under Safe Harbor vs Expert Determination, ignored AI use under the AI controls, and missing metrics under measurement. Tool-first buying is answered in the tooling section, HIPAA-as-governance in the comparison near the top, and unenforced policies in the building blocks.
The fix, then, is to start with authority, because every other control depends on it. Write a one-page charter that says what the council decides, who owns each domain and how disputes escalate. Then ask the executive sponsor to sign it before anyone buys software.
Centralized, Federated or Hybrid: Choosing an Operating Model
An operating model decides where governance decisions are made, whether in one central team, in each business unit or split between them. The right answer depends on how many hospitals, lines of business and data platforms the organization runs.
| Model | Strengths | Weaknesses |
|---|---|---|
| Centralized | One set of definitions, fast decisions and clear accountability | A central team can become a bottleneck as demand grows |
| Federated | Domain experts own their data and move at their own pace | Definitions drift between units without strong shared standards |
| Hybrid | Central standards and tooling with domain ownership of meaning and quality | Needs a clear split of who decides what, or both sides wait on each other |
Hybrid fails in a predictable way. A health system acquires a hospital and adopts central standards on paper. The new hospital keeps its own readmission logic because nobody wrote down which decisions are central, and the three-number meeting returns.
Decision Framework: Which Model for Which Organization
Use the scenario that looks most like your organization today, not the one you plan to become. A model can shift later, but starting with one that fits your current size avoids a year of meetings about structure.
- Single community hospital: pick centralized. One small team can own definitions for one EHR, and decisions stay fast.
- Multi-hospital health system: pick hybrid. Central standards stop every acquired hospital from defining readmission its own way, while local owners keep quality close to care.
- Academic medical center with research: pick hybrid with a research data office. The office handles IRB-linked access and de-identification, so research demand does not overload clinical stewards.
- Payer with many lines of business: pick federated. Medicare Advantage, Medicaid and commercial lines own their data under central standards, so member identity and code sets stay shared.
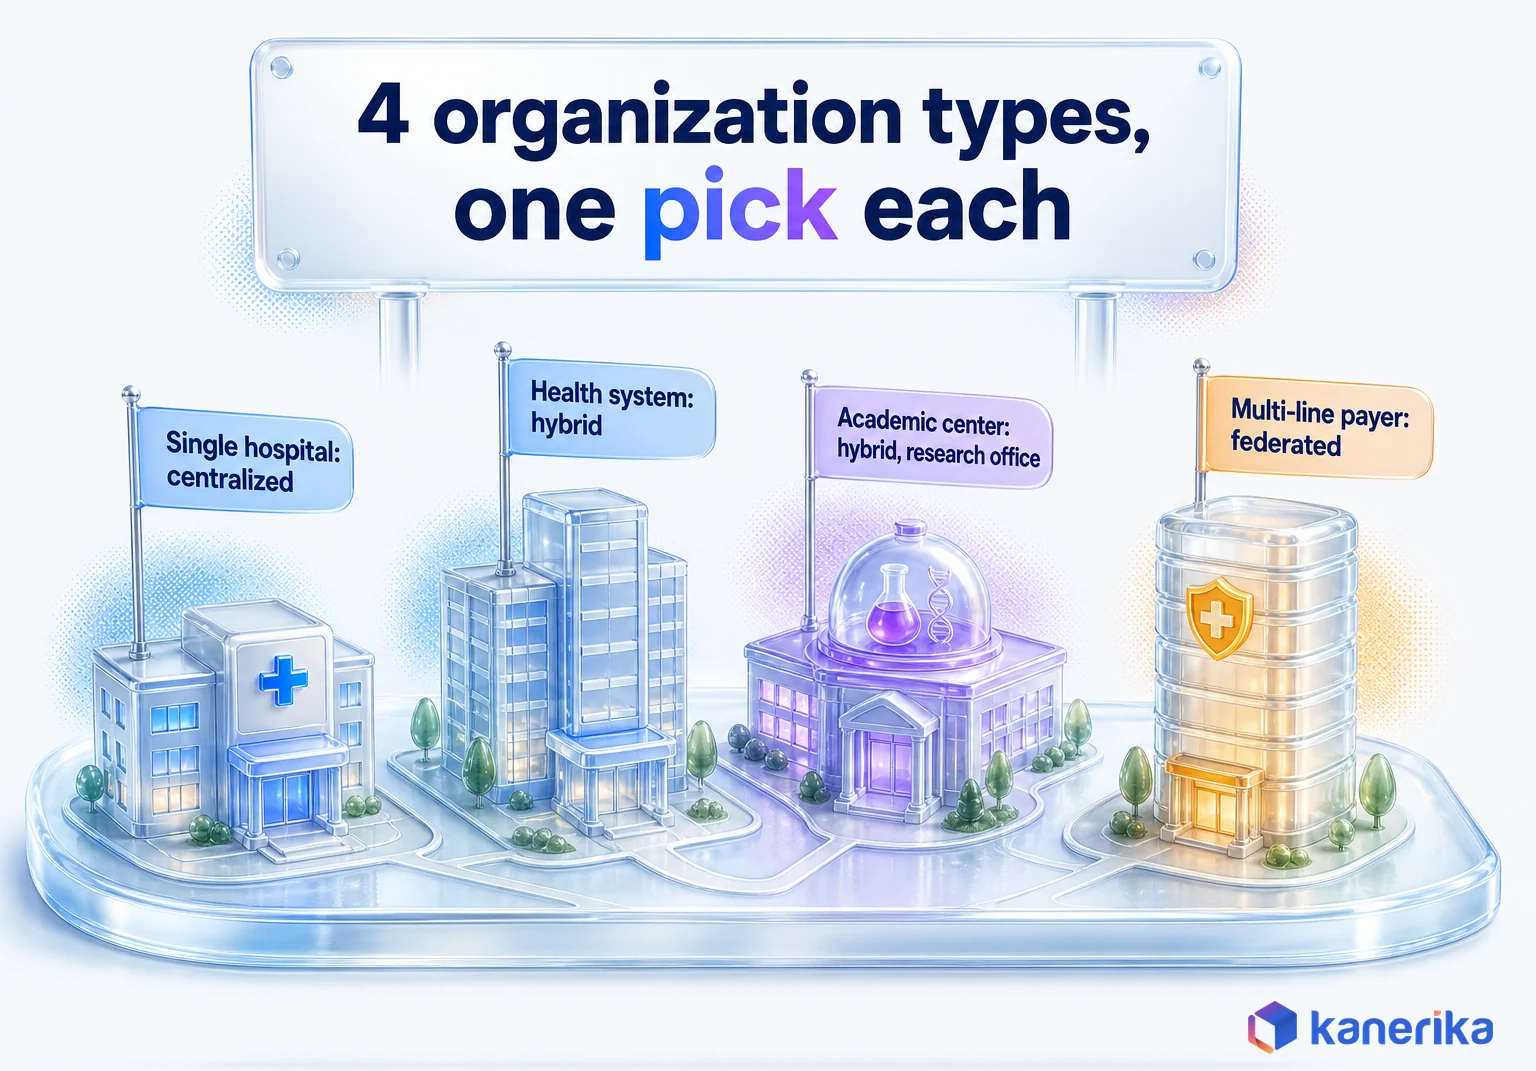
Whatever the pick, write down which decisions are central and which belong to domains. That one page prevents most hybrid failures, because it ends the “I thought you owned that” conversations before they start.
Worked Example: Governing a Readmission-Risk Cohort From Request to Release
A worked example shows how the building blocks fit together on a real request. Suppose the quality team asks for a dataset to build a readmission-risk model for heart failure patients across three hospitals.
The steps below are illustrative and assume a hybrid model with clinical data as the first governed domain.
- Request: the quality analyst submits a request that names the purpose, the fields needed and the planned users.
- Owner sign-off: the clinical domain owner confirms that the purpose is permitted, such as quality improvement under HIPAA health care operations.
- Definition check: the request uses the approved glossary entry for a 30-day readmission, so all three hospitals count the same events.
- Minimum necessary access: the steward removes fields the model does not need, such as full street address and free-text notes.
- De-identification route: because the model team sits outside care delivery, the privacy office decides whether a de-identified extract is required and which method applies.
- Quality checks: rules such as discharge-after-admission and valid diagnosis codes must pass the owner’s thresholds before release.
- Lineage record: the catalog records the source tables, transformations and the approval, so an auditor can trace the dataset later.
- Release and review date: access is granted to named users for a set period, with a review date when the owner confirms continued need.
Why Each Step Matters
Skipping any one step shows up later. Without the definition check, two hospitals report different readmission rates from the same cohort. Without the review date, an analyst who changed roles keeps PHI access for months, which is exactly what a privacy audit flags.
Each step also leaves evidence. So when the model reaches the AI review committee, the team can show where the data came from and who approved it. It can also show how privacy was protected without rebuilding that history from email.
Kanerika Service
Data Governance Services
Kanerika sets up councils, domain owners, classification, quality rules and access controls in Microsoft Fabric, Purview and Databricks, so governance decisions run where your health data lives.
Explore Data Governance ServicesGoverning Health Data for AI and Analytics
AI raises the stakes for data governance because models reuse data at scale and keep what they learn. A report that misuses a field can be corrected next week, while a model trained on the wrong data carries the error into every prediction.
Teams exploring generative AI in healthcare need five data controls in place before training or retrieval starts.
- Training-data provenance: record which sources, dates and filters produced each training set.
- Consent and permitted use: confirm that the purpose fits treatment, payment, operations, research approval or patient authorization.
- Minimum necessary: give models only the fields they need, and keep free-text notes out unless the use case requires them.
- Access for models: treat a model or agent as an identity with its own permissions, under the same data access governance rules as people.
- Logging: keep queries, retrievals and outputs that touch PHI, so the privacy team can investigate later.
However, these controls cover the data side only, a split explained in AI governance vs data governance. Model validation, bias testing and AI oversight committees belong to AI governance in healthcare, which builds on the data controls described here.
Checklist
AI Governance Checklist
Before clinical data feeds a model, check provenance, permitted use, access, validation and logging with Kanerika’s AI governance checklist.
Get the Checklist →De-identification: Safe Harbor vs Expert Determination
HIPAA allows two ways to de-identify health information, and the choice shapes what analysts can still do with the data. Both are defined in 45 CFR 164.514.
| Method | How it works | When to use | Evidence to keep |
|---|---|---|---|
| Safe Harbor, 164.514(b)(2) | Remove the 18 listed identifiers and have no actual knowledge that the rest could identify a person | Broad analytics where dates and small geographies are not needed | The identifier removal checklist, the extract script version and the sign-off |
| Expert Determination, 164.514(b)(1) | A qualified expert applies statistical methods and documents that re-identification risk is very small | Research or models that need dates, ages or finer geography | The expert’s report, methods, assumptions and the conditions of use |
Governance adds one more step that the regulation does not spell out: testing. Before an extract leaves the controlled zone, a steward should scan it for dates, ZIP codes and names in free text. A Safe Harbor extract can drop the date-of-birth column and still carry “patient turned 92 on 3/14” inside a nursing note. That is why free text gets scanned or removed.
Tooling: What a Healthcare Data Governance Stack Needs
Tools enforce governance decisions, but they do not make them. A stack is worth buying only after owners and definitions exist, and then each capability should pass a healthcare-specific test before purchase.
| Capability | What it does | Healthcare test | Example tools |
|---|---|---|---|
| Catalog and glossary | Inventories datasets with owners, definitions and critical data elements | Can a clinician find the approved readmission definition next to the dataset? | Microsoft Fabric OneLake catalog, Databricks Unity Catalog |
| Classification | Tags sensitive data such as PHI and Part 2 records | Do tags follow data into derived tables? | Microsoft Purview |
| Lineage | Traces data from source to report or model | Can an auditor trace a quality measure back to EHR tables? | Microsoft Fabric OneLake catalog, Databricks Unity Catalog |
| Access control and policy | Grants and enforces permissions on data and models | Does access follow minimum necessary by role? | Databricks Unity Catalog, Microsoft Fabric OneLake catalog |
| Data quality | Runs rules and publishes pass rates | Are failures routed to the domain steward? | Microsoft Fabric OneLake catalog |
| Audit logging | Records who queried what and when | Can privacy answer “who saw this record” within a day? | Databricks Unity Catalog audit logs |
How the Two Example Platforms Cover the Stack
Both example platforms cover several rows. Microsoft announced on November 12, 2026 that Purview’s data governance features, including the Unified Catalog, are retiring, with support ending November 12, 2027. Governance moves to the Microsoft Fabric OneLake catalog, while Purview keeps classification, sensitivity labeling and data loss prevention. Databricks Unity Catalog governs data and AI together, enforcing access on queries and model calls while it tracks lineage and logs activity.
The right choice usually follows the data platform you already run, rather than a feature list. Kanerika also compares Unity Catalog, Purview and Collibra side by side. For a wider comparison of options, see this review of data catalog tools and this list of data governance tools.
How to Implement Healthcare Data Governance: A 90-Day Start
A first governed domain can go live in about 90 days when scope stays narrow. The timeline below is a planning assumption for one domain and one use case, not an industry average. Larger estates should also expect each later domain to take its own cycle.
Choose a first use case that leaders can see clearly. A good candidate is a measure that leaders already argue about, such as the readmission rate from the opening scene. Because the dispute is public, a governed answer earns trust quickly. It also hands the council a concrete decision for its first meeting.
Staff the effort lightly but with real names. One domain owner, two stewards, one platform engineer and a privacy reviewer are usually enough for a first domain. They should meet weekly, and the owner should approve each definition in writing so the decision log starts on day one.
The Three Stages and Their Exit Criteria
- Weeks 1 to 3, scope and owners: pick one domain and one live use case. Sign the council charter, then name the domain owner and stewards. Exit when the owner has approved the list of critical data elements.
- Weeks 4 to 8, definitions and rules: write glossary entries first. Then classify PHI and Part 2 data using data classification best practices, and agree on quality rules with thresholds. Exit when every critical element has a definition, a classification and at least one rule.
- Weeks 9 to 12, enforce and report: apply access rules and lineage on the live use case, certify the dataset and publish the first metrics. Exit when the use case runs only on certified data and leaders have seen the scorecard.
Because the first domain becomes the template for the rest, resist adding a second before week 12. Finishing it properly saves time on every later one.

How to Measure Data Governance in Healthcare
Metrics tell leaders whether governance changes behavior or only produces documents. Five measures cover ownership, quality, speed and trust, and each can be calculated from the catalog and access logs.
| Metric | Formula | Target direction |
|---|---|---|
| Owner coverage | Critical data elements with a named owner divided by all critical data elements | Up, toward 100% |
| Quality rule pass rate | Records passing a rule divided by records checked, per critical element | Up, at or above the owner’s threshold |
| Access approval time | Median days from data access request to approval or denial | Down |
| Certified report share | Reports built on certified datasets divided by all active reports | Up |
| Open policy exceptions | Count of approved exceptions past their review date | Down |
Report these each quarter to the council and the executive sponsor. Over time, the same numbers show progress along a data governance maturity model. If owner coverage rises but the pass rate stays flat, owners exist on paper only, and the council should ask why.
Certified datasets also make later reporting work easier, for example during a BI migration for healthcare. In that case, migrated reports point at governed sources instead of copying old logic. The same applies when teams move to Microsoft Fabric for healthcare.
How Kanerika Delivers Healthcare Data Governance
Kanerika helps healthcare organizations turn governance from a policy set into controls that run in the data platform. The work follows five stages, and each one ends with evidence a council can review.
- Assess: map current data sources, owners, sensitive data and the rules that apply to them.
- Define: set up the council, name domain owners and write definitions, classifications and policies.
- Enforce: configure the catalog, classification, access rules and quality checks in the platform.
- Prove: publish lineage, quality pass rates and owner coverage so leaders can see progress.
- Scale: repeat the template domain by domain, reusing the standards built for the first one.
A top North American healthcare organization with hospitals, clinics and specialty centers shows how this works. Its data was spread across Azure Blob Storage, SQL databases and SaaS applications, with no consistent classification or metadata framework. Kanerika built a Microsoft Purview catalog with metadata and classifications. It also set up a classification framework with steward roles and usage policies, plus Power BI dashboards backed by user guides.
The project delivered a 57% reduction in data discovery time and a 90% increase in compliance adherence. It also brought a 70% enhancement in data accessibility, as described in the healthcare Purview case study.
Talk to Kanerika
Plan Your First Governed Healthcare Domain
Book a working session with Kanerika to scope one domain, name its owners and design the controls and metrics for a 90-day start.
Schedule a Demo →Teams that want help with the first domain can start with Kanerika’s data governance services.
Bottom Line: Fix Ownership Before Tools
Teams get data governance wrong when they treat it as a compliance binder, a committee or a software purchase. They get it right when named owners make decisions and the platform enforces those decisions on real data.
Start small and specific. Choose one domain, pick the operating model that fits your organization today, and measure owner coverage and quality within 90 days. The fix starts this quarter: a signed charter and one named owner for the domain your leaders argue about most.
Frequently Asked Questions
What is the role of data governance in healthcare?
Data governance in healthcare decides who owns patient, claims and operational data, what each field means and who may use it. It then turns those decisions into controls inside the data platform. The result is one trusted version of key measures, such as readmissions, plus evidence that privacy rules are followed whenever data is reused.
Why is data governance important in healthcare?
Healthcare data drives treatment, billing and research, so a wrong or misused field causes real harm. Governance keeps definitions consistent across hospitals and systems, controls access to protected health information and records who used data for what. It also supplies the evidence that HIPAA, 42 CFR Part 2 and CMS interoperability rules expect an organization to show.
What is the difference between data governance and data management in healthcare?
Data governance decides the rules, such as who owns encounter data, what a readmission means and who may access PHI. Data management carries out the work, such as building pipelines, storing records and maintaining databases. Governance is usually led by business and clinical owners, while data management sits with IT and data engineering teams who follow the rules.
Should a health system use centralized or federated data governance?
It depends on structure. A single community hospital usually does best with a centralized model and one small team. A multi-hospital health system fits a hybrid model, with central standards and local domain owners. Payers with many lines of business fit federated ownership under shared standards for member identity, code sets and core definitions.
What tools are used for healthcare data governance?
A healthcare governance stack needs a catalog and glossary, classification, lineage, access control, data quality checks and audit logging. Microsoft Purview Unified Catalog and Databricks Unity Catalog each cover several of these. Choose tools only after owners and definitions exist, and test whether sensitive data tags such as PHI follow data into derived tables.
How long does it take to implement healthcare data governance?
A first governed domain can go live in about 90 days when scope stays narrow. That plan assumes three weeks to name owners, five weeks for definitions and quality rules, and four weeks to enforce controls on one live use case. Each later domain runs its own cycle, so a whole program takes considerably longer.
How do you measure healthcare data governance success?
Track five measures every quarter. These are owner coverage for critical data elements, quality rule pass rates, median time to approve data access requests, the share of reports built on certified datasets and open policy exceptions past review. Rising owner coverage with a flat pass rate is a warning sign that owners exist only on paper.
How does data governance support AI in healthcare?
Governance gives AI teams data they are allowed to use and can trust. It records training-data provenance, checks consent and permitted use, limits fields to minimum necessary and logs every query that touches PHI. Model validation and bias testing sit under AI governance, which depends on these data controls being in place first.
How do you de-identify patient data for analytics?
HIPAA allows two methods under 45 CFR 164.514. Safe Harbor removes 18 listed identifiers, such as names, most dates and small geographic units. Expert Determination uses a qualified expert to show that re-identification risk is very small. Whichever route you use, keep the evidence and test each extract for leftover dates or names in free text.
How does data governance improve patient care?
Governance improves care by making clinical data trustworthy enough to act on. When owners approve definitions and quality rules check key fields, dashboards for readmissions, sepsis or falls show the same numbers everywhere. Clinicians then spend meetings on improvement instead of arguing about whose report is right, and care teams can share accurate records across settings.
What are the pillars of data governance in healthcare?
Most frameworks rest on five pillars. These are decision rights with named owners, data domains, standards and definitions, data quality rules, and metadata with lineage. Privacy and security act as guardrails across all five. Owners come first, because every other pillar needs someone with authority to approve definitions, thresholds and permitted uses for each domain.
How is clinical governance different from data governance?
Clinical governance is the system that keeps patient care safe and effective, covering areas such as clinical audit, risk management, staff training and patient involvement. Data governance is narrower. It manages the data those activities depend on, including ownership, definitions, quality and access. Strong clinical governance relies on governed data, but the two have different owners.
What are the main roles in healthcare data governance?
The main roles are an executive sponsor, a chief data or analytics officer, a governance council, domain owners, data stewards and data custodians. Domain owners decide what data means and who may use it. Stewards maintain rules and fix issues day to day. Custodians build the controls, while privacy officers set guardrails for everyone.
What is an example of data governance in healthcare?
A common example is a governed readmission dataset. The clinical owner approves one definition of a 30-day readmission for every hospital. Stewards run quality rules, such as discharge after admission. Access follows minimum necessary, and lineage records each source table. Every dashboard and risk model then uses the same certified numbers with a clear audit trail.
What are the first phases of a healthcare data governance program?
The first phase is scoping one domain and naming its owner and stewards under a signed council charter. Next, the team writes definitions, classifies sensitive data and agrees on quality rules. The third phase enforces access and lineage on one live use case. The last phase reports metrics and repeats the template for the next domain.
What are the goals of data governance in healthcare?
The goals are trusted data for care and decisions, protected patient privacy and evidence for regulators. Programs also aim for consistent definitions across hospitals, faster and safer data access for analytics, fewer billing errors from data mismatches and clean exchange with payers and partners. Each goal should map to a metric the council reviews every quarter.
Is HIPAA compliance the same as data governance?
No. HIPAA compliance proves that protected health information is handled within federal privacy and security rules. Data governance is broader. It also decides what data means, who owns each domain, which quality thresholds apply and how data may be reused. HIPAA does not define a readmission or name a steward, so compliance alone leaves those gaps open.












